
New patient forms.

Save time at your first visit. Preview or download the packet, print it, and bring your completed forms to your appointment. You can also fill them out at the office.

Your 2026 new patient packet.

The packet includes patient intake and medical information. Fill it out by hand and bring it to your appointment. Completing it ahead of time is optional.

6 pages · PDF · 10.9 MB · US Letter (8.5 × 11 inches). Preview opens in a new tab. Print and fill out by hand; this PDF does not submit information online.

Read the packet content on this page
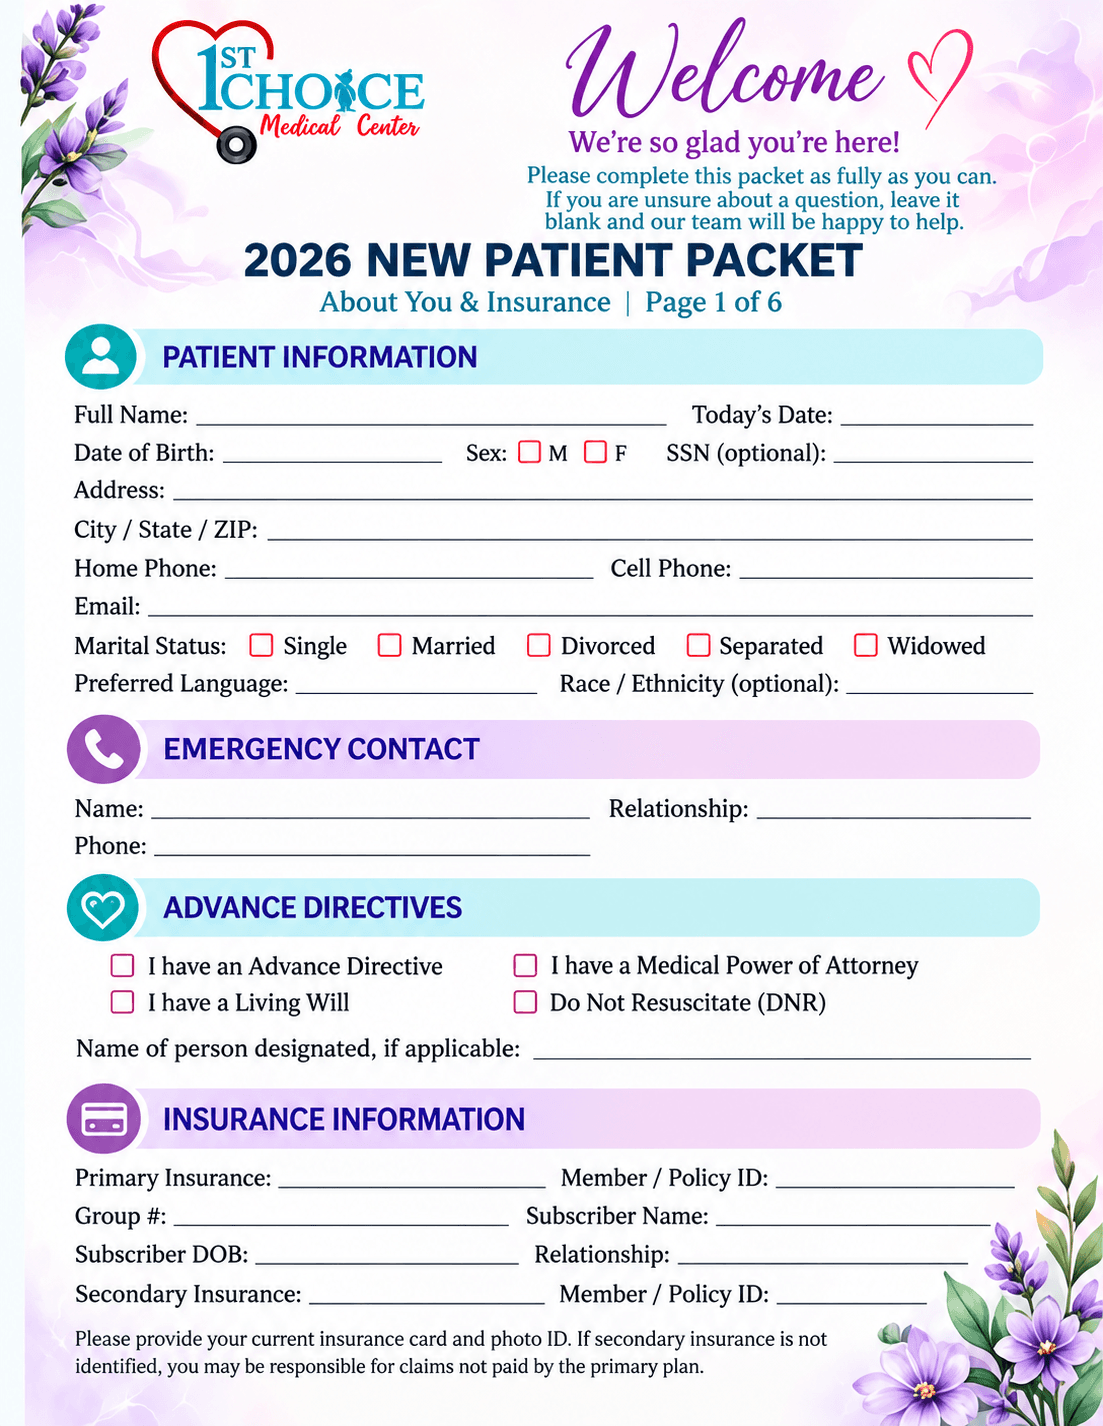
Floral cover of the 2026 First Choice new patient packet.
The clinic’s six-page floral packet.

What’s in your packet.

Read the fields and policy statements below. These sections are for reference; complete and sign the printed packet. If you are unsure about a question, leave it blank and ask the office for help.

Page 1 of 6 About you & insurance

Patient information

Full name; today's date; date of birth; sex (M / F); SSN (optional); address; city / state / ZIP; home and cell phone; email; marital status (single, married, divorced, separated, widowed); preferred language; race / ethnicity (optional).

Emergency contact

Name, relationship, and phone number.

Advance directives

Indicate whether you have an Advance Directive, Living Will, Medical Power of Attorney, or Do Not Resuscitate (DNR). Name of person designated, if applicable.

Insurance information

Primary insurance; member / policy ID; group number; subscriber name; subscriber date of birth; relationship; secondary insurance and member / policy ID. Please provide your current insurance card and photo ID. If secondary insurance is not identified, you may be responsible for claims not paid by the primary plan.

Page 2 of 6 Medications, allergies & medical history

Pharmacy

Pharmacy name / location and phone number.

Current medications & supplements

List each medication or supplement, dose / strength, and how often you take it.

Allergies / intolerances

List each medication or substance and your reaction.

Medical history

Indicate any of the listed conditions: Anemia / COPD; Anxiety / Depression; Arthritis; Asthma; Cancer; Chronic Fatigue; Diabetes; Heart Disease; High Blood Pressure; High Cholesterol; Kidney Disease; Liver Disease; Migraines; Seizure Disorder; Stroke / CVA; Thyroid Disorder; Urinary Problems; or Other. Anything else about your health that you want your provider to know?

Page 3 of 6 Past history, family & lifestyle

Surgeries / hospitalizations

Year / date and surgery or reason for hospitalization.

Family history

Diabetes; High Blood Pressure; High Cholesterol; Heart Disease; Cancer; Mental Health Condition; Stroke; or Other. For any checked condition, who in your family?

Social & lifestyle history

Tobacco (never, current, former), amount / quit date; alcohol (no / yes), approximate drinks per week; recreational drugs (no / yes), type if yes; caffeine (none, 1–2/day, 3+/day); exercise (no / yes), days per week; diet (regular / special diet), description; living situation (married, separated, single, other).

Women's health — if applicable

Periods (regular, irregular, menopausal); last period; last Pap smear; abnormal Pap (yes / no); last mammogram; pregnancies (G); live births (P); miscarriages; C-sections; other OB/GYN history.

Page 4 of 6 Preventive care & communication preferences

Immunizations

Indicate yes / no and approximate date for Tetanus / Tdap; Pneumococcal; Influenza; Shingles (Zostavax/Shingrix); and Other.

Preventive care

Indicate whether done (yes / no) and approximate date for vision exam; osteoporosis screening; colorectal cancer screening; cholesterol test; blood sugar / glucose; hemoglobin A1c; and other labs / screening.

How may we contact you?

Please tell us how you prefer to receive routine communication and appointment reminders: call home, call cell, text message, email, or patient portal. Preferred phone and email. May we leave a detailed message (yes / no)? May we leave a voicemail with appointment information (yes / no)? People we may share medical information with (optional): name and phone. Patient signature and date.

Page 5 of 6 Consent, privacy & financial policies

Consent for care

I authorize First Choice Medical Center to provide medical care and treatment as deemed necessary by my provider. I understand that I am responsible for providing accurate and complete information. I agree to inform the office of any changes in my health, medications, or insurance.

Acknowledgment of privacy practices (HIPAA)

I have received a copy of the Notice of Privacy Practices. I understand how my protected health information may be used and disclosed.

Financial policy

I understand that I am responsible for all charges not covered by my insurance. I agree to pay copayments, deductibles, and any non-covered services at the time of service. I understand that insurance is a contract between me and my insurance company and that I am ultimately responsible for payment. I understand there may be additional charges for forms, documentation, or other services not covered.

Assignment of benefits

I authorize payment of medical benefits directly to First Choice Medical Center for services rendered. I authorize release of any medical information necessary to process my insurance claims. Patient signature and date.

Page 6 of 6 Additional information

Reason for today's visit

Please tell us the main reason for your visit and any specific concerns you would like to discuss.

Goals for your health

What are your health goals? Examples: better energy, weight management, hormone balance, skin health, preventive care, etc.

Additional notes

Is there anything else you would like your provider to know?

Completing forms through Healow?

If you receive a Healow check-in message for your appointment, follow its link to complete the available forms online. You can book first and complete paperwork later, when check-in is available.

Bring any paper forms to your visit. Please do not send completed forms or medical information by ordinary email.

Have these details nearby.

  • Your contact details and an emergency contact.
  • Medications, supplements, allergies, and relevant health history.
  • Previous procedures and the concerns you would like to discuss.

If you are unsure about an answer, ask the office for help.

Still need an appointment?

Book your consultation now. You can complete the forms later.

Book a consultation

Questions about your paperwork

Do I need to complete forms before booking?

No. You can book or request your appointment first. Completing paperwork online ahead of your visit is optional. The office can help you complete the information and any required consents before your care.

Where do I complete my online forms?

If you receive a Healow check-in message for your appointment, follow its link to complete the available forms online. Availability depends on your appointment and patient record. You can also print the intake and bring it with you, or complete your paperwork at the office.

Can I fill out forms before I have an appointment?

Yes. You can preview, download, and print the blank intake packet at any time. Fill it out by hand and bring it to your visit. This PDF does not submit information online, and you do not need to complete it before booking.

What if I prefer paper or need help?

Print the intake packet and bring your completed pages, along with a current medication and supplement list. You can also complete paperwork at the office, where our team can help with questions.